
GP assessment
Your GP reviews the symptoms, examines the hip and starts appropriate non-surgical care. Exercise, weight management where relevant and pain treatment remain useful even if referral is later needed.
If you searched for “hip replacement near me” in Swansea, this consultant-written guide gives you a clear local answer. It explains when total hip replacement may be considered, how the Swansea Bay pathway works, where care may take place and how to prepare well for surgery.
If you are looking for hip replacement in Swansea, a “near me” search is usually asking three questions at once: do my symptoms sound severe enough for surgery, who provides care locally, and what happens next? This page answers those questions for people in Swansea, Neath and Port Talbot.
Hip replacement is not recommended from an X-ray alone. The decision is based on the pattern and severity of your pain, stiffness and loss of function; the effect on sleep, work and independence; what non-surgical treatment you have tried; your general health; and what you want surgery to achieve.
If your main question is about the implant, surgical approach, benefits, risks or long-term results, use the detailed total hip replacement patient guide. If you are already listed for surgery, the hip replacement recovery guide explains the first days, walking, precautions, work, driving and rehabilitation.
Hip osteoarthritis can present differently from person to person. Common features include deep groin pain, stiffness and a gradual loss of confidence in ordinary movement.
Some of these symptoms can also come from the lumbar spine, tendons at the side of the hip or other conditions. A careful history and examination therefore matter. Weight-bearing X-rays are often helpful when surgery is being considered, but the scan or X-ray must be interpreted alongside your symptoms rather than treated as the decision by itself.
Referral should be individual. NICE advises considering referral for joint replacement when pain, stiffness, reduced function or progressive deformity substantially affects quality of life and non-surgical management is ineffective or unsuitable. It also advises against excluding someone from referral solely because of age, sex or gender, smoking, comorbidities, or overweight or obesity. Personal risks still need an honest discussion and should be improved where possible.
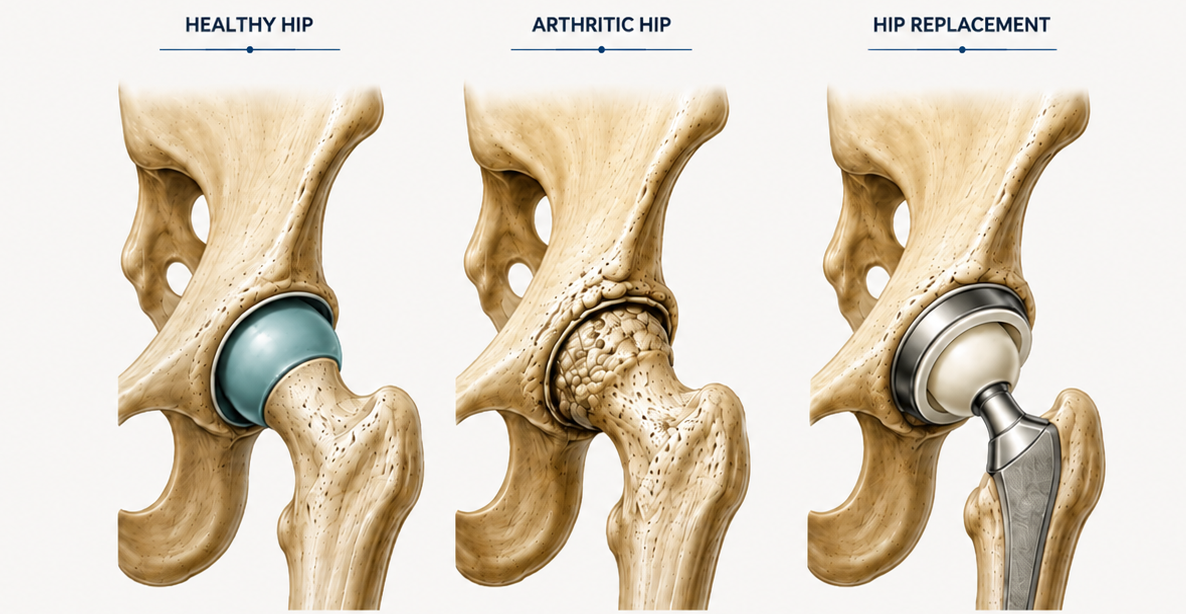
The hip is a ball-and-socket joint. In a total hip replacement, the worn femoral head is removed, a stem is placed inside the thigh bone, a new ball is attached, and the damaged socket is resurfaced with an artificial cup and liner.
The aim is to reduce arthritic pain and improve function. It does not make the hip biologically young again, and no operation can guarantee a particular walking distance, range of movement or lifetime result.
The detailed guide covers hip arthritis, alternatives to surgery, implant fixation, surgical approach, anaesthesia, risks, outcomes and implant longevity. Keeping that technical material on one authoritative page avoids conflicting advice and makes it easier to update.
Explore total hip replacementThe precise route can vary, but most patients move through the same six stages. Your appointment letters and the advice from your treating team always take priority over a general website.
Your GP reviews the symptoms, examines the hip and starts appropriate non-surgical care. Exercise, weight management where relevant and pain treatment remain useful even if referral is later needed.
The referral is reviewed and directed to the appropriate musculoskeletal or orthopaedic pathway. Previous hip surgery or an existing replacement should be clearly stated.
Your history, walking, hip movement and imaging are considered together. The clinician checks that the hip joint is the main source of pain and discusses reasonable alternatives.
If hip replacement is appropriate, the expected benefit, important risks and rehabilitation commitment are discussed. Choosing to continue non-surgical treatment is also valid.
Blood tests, medicines, anaesthetic risk, home circumstances and modifiable health factors are reviewed. Some problems need treatment before an operation can proceed safely.
Mobilisation usually begins on the day of surgery or the following day. Discharge is based on safe walking, controlled pain, a stable wound and suitable support at home.
Hip replacement care within Swansea Bay University Health Board is delivered across Neath Port Talbot Hospital and Morriston Hospital. The right site depends on the planned procedure, your health needs and the facilities required.
Neath Port Talbot Hospital provides outpatient, inpatient and day-case services and is a major site for planned orthopaedic care within Swansea Bay. Many routine elective hip replacement pathways are centred here.
Morriston Hospital provides acute trauma, specialist surgical and critical-care support. Some complex or higher-risk orthopaedic operations are planned there when that wider infrastructure is required.
Your appointment letter is the definitive guide. Clinics, operating lists and hospital arrangements can change. Do not travel to a site because it is mentioned on this page; use the location, date and contact details in your own letter.

This local hip replacement guide is written and clinically reviewed by Mr Atanu Bhattacharjee, a consultant at Swansea Bay University Health Board whose practice focuses on primary and complex hip and knee replacement, revision surgery and periprosthetic reconstruction.
Qualifications: MBBS, MRCS, MSc, PhD, Dip Orth Oncology, FRCS (T&O) · GMC: 6096723
Read about Mr Bhattacharjee’s specialist training, research and approach to hip replacement surgery.
You begin recovery from the level of strength, fitness and support you have on the day of surgery. Preparation does not remove every risk, but it can make the early weeks safer and more manageable.
Use activity that your hip tolerates, such as short walks, a stationary bicycle, swimming or prescribed exercises. Aim to maintain leg, core and upper-body strength rather than pushing through severe pain.
Stopping smoking, improving diabetes control, treating anaemia or dental infection, moderating alcohol and addressing nutrition can reduce avoidable problems. Ask for professional support early.
Clear trip hazards, choose a firm chair with arms, move everyday items within reach, plan meals and arrange transport and help. Practise with crutches if the therapy team offers this.
Do not stop anticoagulants, steroids, diabetes medicines or other prescribed treatment without an individual plan from the surgical or pre-assessment team.

Most people are helped to stand and walk soon after surgery. The arthritic joint pain may improve quickly, while surgical soreness, muscle weakness, stamina and confidence recover over weeks and months.
Standing and walking with a frame or crutches, pain control and practising transfers and stairs where needed.
Short regular walks, prescribed exercises, wound protection and balancing activity with rest.
Gradually longer walks, progressive strengthening and return to daily activity, driving and work when safe.
Continuing improvement in strength, balance, endurance, gait and confidence. Progress varies considerably.
Recovery is individual. Age, fitness, other medical conditions, the complexity of the operation, support at home and early complications all influence pace. Read the full hip replacement recovery guide for South Wales rather than using a single date as a target.
If you have persistent hip or groin pain, start with your GP or the local musculoskeletal pathway. Your GP can assess for other causes, review pain treatment, support exercise and weight management where relevant, request investigations when indicated and refer for an orthopaedic opinion when appropriate.
If you are already on a Swansea Bay waiting list, use the contact details in your hospital letter for questions about your appointment or operation. The health board publishes changing outpatient waiting-time information, but only your treating service can advise about your individual position.
This website provides patient education and does not replace a referral, consultation or advice from the team responsible for your care.
Call 999 for a medical emergency. For urgent advice that is not life-threatening, contact your GP or NHS 111 Wales.
These answers are general. Your own surgeon, anaesthetist and therapy team may give different advice because they know your diagnosis, operation and health.
Within Swansea Bay University Health Board, planned orthopaedic care is commonly provided at Neath Port Talbot Hospital, while Morriston Hospital provides acute, specialist and critical-care support for cases that need it. The location in your appointment or admission letter is definitive because service arrangements can change.
NHS assessment normally begins through your GP or the local musculoskeletal pathway. The referral is triaged to the appropriate service. If you have previous hip surgery, an existing replacement, infection concerns or a fracture, make that clear because it can change the pathway.
You can discuss your preference with your GP, but NHS referral arrangements vary and a referral may be made to a service rather than guaranteed to one clinician. Urgency, clinical need, subspecialist expertise and available capacity can all influence allocation.
Hip-joint pain is often felt in the groin, front of the thigh or knee and may be accompanied by stiffness, a limp and difficulty with shoes and socks. Back, nerve or tendon problems can mimic hip arthritis. Diagnosis therefore needs history and examination, with imaging where appropriate.
NICE advises that people should not be excluded from referral solely because of age, sex or gender, smoking, comorbidities, or overweight or obesity. These factors may alter personal risk and the preparation needed, so they still require an individual discussion.
Waiting times change and depend on clinical priority, hospital capacity and the type of surgery required. Swansea Bay publishes general waiting-time information, but it cannot predict an individual operation date. Ask the treating service using the details in your letter.
Many patients go home within one to three days after an uncomplicated primary hip replacement. Some leave sooner and others need longer. Discharge depends on safe mobility, pain control, wound and medical stability, and the support available at home rather than a fixed number of nights.
Maintain tolerable activity and strength, stop smoking, improve diabetes control and nutrition, address dental infection, review medicines at pre-assessment, prepare the home and arrange practical support. Do not start an extreme diet or stop prescribed medicines without clinical advice.
A painful existing replacement needs a different assessment from first-time hip arthritis. Causes can include infection, loosening, wear, instability, fracture or pain coming from elsewhere. Read the revision hip and knee replacement guide and seek review through your GP or treating orthopaedic team.
Consultant Orthopaedic Surgeon, Swansea Bay University Health Board. Specialist interests include primary and complex hip and knee replacement, revision arthroplasty, periprosthetic fracture surgery and complex lower-limb reconstruction.
Important: This page is general patient information, not a diagnosis or a recommendation for surgery. The right treatment can only be decided after personal assessment. In an emergency, call 999 or attend the nearest emergency department.
