Hip Replacement

Total Hip Replacement: Six Essential Facts

  • What does a total hip replacement involve: The worn hip joint is replaced with an artificial socket, ball and stem.
  • When is it considered: When hip pain and loss of function significantly affect quality of life despite appropriate non-surgical treatment.
  • Reported improvement: Around 95 in 100 patients reported improvement after surgery (NHS England, 2024/25).
  • How long implants last: Around 94% remain unrevised at 20 years and 92% at 30 years (2026 global registry study).
  • Recovery: Walking usually begins soon after surgery. Many patients go home within one to three days, although full recovery takes several months.
  • Important risks: These include infection, dislocation, blood clots, fracture, nerve injury, leg-length difference and persistent pain.


The hip is a ball-and-socket joint. Smooth cartilage normally allows the ball at the top of the thigh bone (femoral head) to move easily inside the socket in the pelvis (acetabulum). In hip osteoarthritis, this cartilage and the bone beneath it gradually change. The joint becomes painful and stiff, movement becomes restricted, and the surrounding muscles often weaken as activity falls.

Common symptoms include:

  • groin, buttock or thigh pain, sometimes felt in the knee
  • pain on walking, on stairs or when getting in and out of a car
  • difficulty putting on shoes and socks or cutting toenails
  • stiffness after sitting, and pain that disturbs sleep
  • a limp, reduced walking distance, or loss of confidence outdoors

Symptoms do not always match how severe the arthritis looks on an X-ray. NICE notes that osteoarthritis is often diagnosed clinically and that routine imaging is not always used to support the diagnosis and plan a shared treatment strategy.

NICE recommends considering referral for joint replacement when symptoms such as pain, stiffness, reduced function or progressive deformity are substantially affecting quality of life, and non-surgical management has been ineffective or is unsuitable. The decision should be based on clinical assessment rather than an arbitrary numerical score or an X-ray alone.

  • Pain, stiffness or loss of function still matters to you despite appropriate treatment.
  • Your symptoms and examination are consistent with hip joint disease, supported by imaging where appropriate.
  • You understand what surgery can and cannot achieve, and the recovery commitment is acceptable to you.
  • Your general health has been assessed, and modifiable risks have been addressed where possible.

BOA and British Hip Society good-practice guidance also emphasises adequate consultation time, a clear and documented consent discussion covering implant choice, and pre-admission assessment as part of a well-run hip replacement pathway.

Non-surgical care remains worthwhile whether you are trying to avoid surgery, waiting for it, or preparing for it. A combined plan usually works better than relying on a single treatment.

Exercise and physiotherapy

Therapeutic exercise is a core treatment. NICE recommends exercise tailored to the individual, including local muscle strengthening and general aerobic fitness. Strength, balance and aerobic work may feel uncomfortable at first, but a gradual programme can reduce pain and improve function. Manual therapy should be used alongside exercise, not instead of it.

Weight management, walking aids and daily habits

If you are living with overweight or obesity, weight loss reduces the load on your joints and improves overall health. NICE advises that any weight loss can help, and that, where achievable, losing around 10% of body weight is likely to yield greater benefit than losing 5%. A walking stick used in the opposite hand, a footwear review, pacing, and adapting demanding tasks can all conserve energy and improve safety.

Medicines and injections
  • A topical anti-inflammatory (NSAID) may be tried, though it is generally less effective for the hip than for more superficial joints due to the hip’s depth.
  • An oral NSAID may be considered after reviewing stomach, kidney, liver and cardiovascular risks, usually with gastroprotection, at the lowest effective dose for the shortest suitable period.
  • Paracetamol and weak opioids are not routinely recommended, except for infrequent short-term use when other options are unsuitable. Strong opioids are not recommended for osteoarthritis.
  • An image-guided corticosteroid injection into the hip joint can give short-term relief for some people. NICE advises explaining that the benefit is usually short-term, around 2–10 weeks. An injection into the joint is a different procedure from an injection at the side of the hip for trochanteric pain.
Treatments not routinely recommended

NICE does not recommend hyaluronan injections, glucosamine, strong opioids, or acupuncture and dry needling for osteoarthritis. Non-surgical measures can relieve symptoms and delay surgery, but they do not reverse established joint damage.

If you decide to wait

Hip osteoarthritis is not usually dangerous. Symptoms may stay similar, fluctuate or worsen. Continue the agreed exercise and symptom-control plan, and ask for reassessment if pain, sleep, walking, stiffness, or independence change. Choosing not to have surgery is a valid decision.

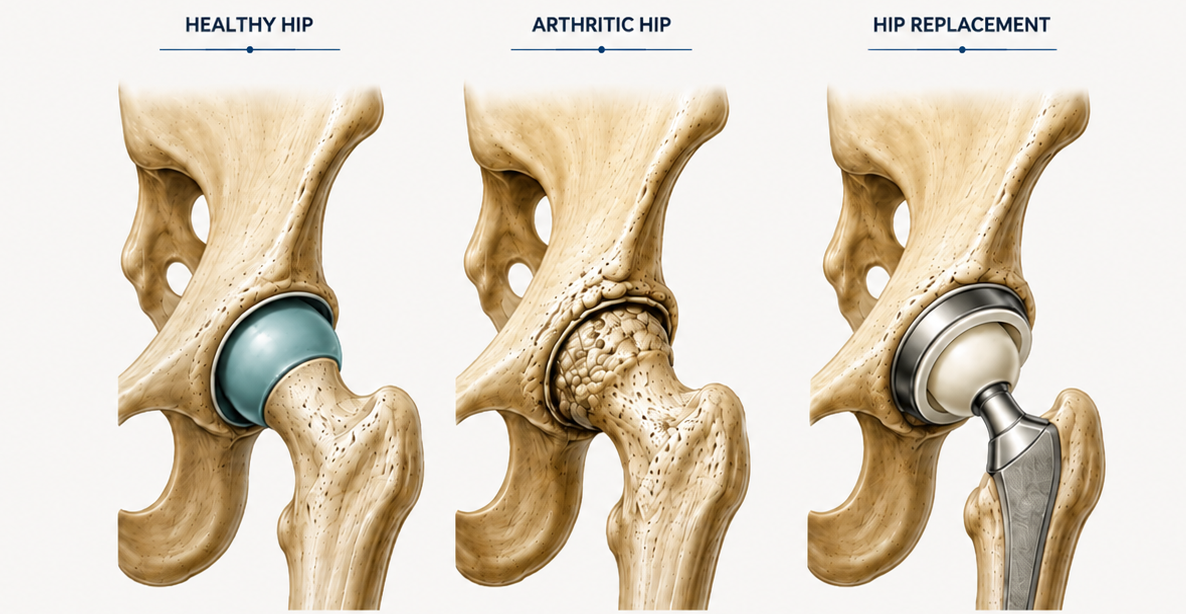
The surgeon removes the worn femoral head and prepares the socket in the pelvis. An artificial socket is fitted into the pelvis, a stem is placed inside the thigh bone, and a new ball is attached to the stem to articulate with the socket. Component sizes and positions are chosen to restore stability, movement and leg length as closely as possible.

Surgical approach

NICE recommends considering a posterior or anterolateral approach for primary elective hip replacement. There was insufficient evidence for NICE to make recommendations on the direct anterior, direct superior, or SuperPATH approaches. I use the posterior approach for hip replacement because it produces consistent outcomes for my patients.

Anaesthesia and pain relief

NICE recommends offering a choice between regional anaesthesia (usually spinal) and general anaesthesia, combined with local infiltration analgesia around the hip. Your anaesthetist will discuss the options and your individual risks.

Blood loss and infection prevention

NICE recommends tranexamic acid for primary elective hip replacement to reduce blood loss, with the dose and route adjusted according to kidney function. Antibiotic prophylaxis and surgical-site infection precautions are used around the operation, together with ultra-clean air ventilation for elective joint replacement.

No operation is risk-free. Your surgeon and anaesthetist should explain which risks matter most to you, considering age, frailty, smoking, diabetes, weight, heart, lung and kidney disease, medicines, previous surgery and bone quality.

Expected or usually temporary effects
  • Pain, bruising, swelling, fatigue, disturbed sleep and reduced mobility in early recovery.
  • A scar, and often a numb or altered-feeling patch of skin beside it.
  • A need for walking aids and help with some everyday activities for a period.

Important hip-specific risks

Infection

A superficial wound problem may settle with treatment. Deep infection around the implant may require a washout, prolonged antibiotics, or revision surgery. NJR patient information describes infection after joint replacement as rare, occurring in fewer than 1% of cases.

Dislocation

The ball can come out of the socket, usually in the early months and often with a particular combination of movements. It may need to be put back under anaesthetic, and repeated dislocation can require further surgery.

Leg-length difference

Restoring stability sometimes results in a small difference in leg length. Most are minor and settle as you adjust; a shoe raise occasionally helps.

Fracture

The femur or the pelvis can crack during or after surgery and may need fixation, wires or a different implant. A periprosthetic fracture can also occur later, usually after a fall.

Blood clot: Deep Vein Thrombosis(DVT) or Pulmonary Embolism(PE)

Early mobilisation and preventive medication reduce, but do not remove, the risk.

Nerve or blood-vessel injury

Injury to the sciatic or femoral nerve can cause numbness, weakness or foot drop. This is uncommon but can be serious and is not always fully reversible.

Wear, loosening or implant failure

A replacement may eventually need revision surgery. NICE recommends prostheses with revision rates (or projected rates) of 5% or less at 10 years.

Persistent pain

Some people continue to have pain despite a well-positioned implant, sometimes from the tendons and muscles at the side of the hip  and chronic low back rather than the joint itself.

Trochanteric or abductor pain

Pain and tenderness over the bony point at the side of the hip, sometimes with a limp, which usually improves with physiotherapy.

Heterotopic ossification

Extra bone can form in the soft tissues around the hip, occasionally reducing movement.

General surgical and medical risks
  • Bleeding, haematoma or the need for a blood transfusion.
  • Urine retention or urinary infection, chest infection, kidney problems, medication reactions or pressure damage to skin.
  • Heart attack, stroke, serious anaesthetic complication or death. These are uncommon, but personal risk is higher with some medical conditions.

  • Attend pre-operative assessment and give the team a complete list of medical conditions, allergies, medicines, supplements and previous anaesthetic problems.
  • Do not stop blood thinners, diabetes medicines, steroids or immune-modifying treatment unless the surgical team gives you a specific plan.
  • Build strength and stamina within your limits. NICE recommends preoperative rehabilitation advice covering exercise, lifestyle, diet, weight management and smoking cessation.
  • If you smoke, stopping reduces wound, lung and infection risks. Ask for NHS stop-smoking support if needed.
  • If you have diabetes, good blood-glucose control helps reduce complications. Anaemia, poor nutrition and dental infection should be addressed where possible.
  • Tell the team about fever, a new infection, broken skin, ulcers or a worsening wound before admission. Keep the leg skin clean with 2% Chlorhexidine wipes (off-the-shelf) for 2-3 days before surgery.
  • Shower or bathe as instructed. Do not shave or wax the operation area unless specifically told to do so; hospitals use safe hair-removal methods if needed.
  • Prepare your home: clear trip hazards, consider chair and bed height, put frequently used items within easy reach, plan meals, arrange transport and identify someone who can help during the first days.
  • Practise using crutches or a frame beforehand if the physiotherapist offers this.
